
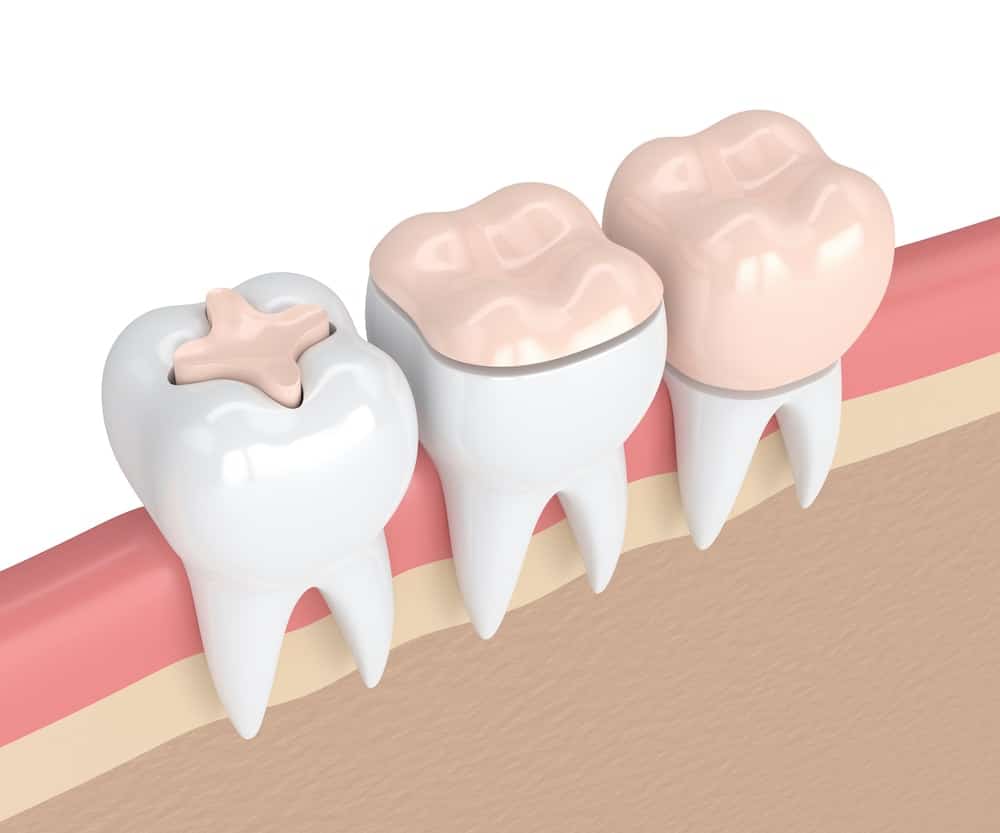
Dental crowns provide full coverage for teeth that are severely damaged, cracked, or treated with a root canal, while other restorations like fillings, inlays, onlays, veneers, and bonding repair only part of the tooth. The difference comes down to how much of the tooth each option covers and how much healthy tooth structure is left to work with. A filling replaces decayed material inside a cavity. An inlay or onlay rebuilds a portion of the chewing surface. A veneer resurfaces the front of a tooth. A crown encases everything above the gumline. Below we compare each option side by side, show what the survival data says about how long each one lasts, explain how much tooth structure each one removes, and lay out the situations where a crown is the right call.
What Is the Difference Between Dental Crowns and Other Restorations?
The difference between dental crowns and other restorations is coverage. A dental crown covers the entire visible tooth above the gumline, while fillings, inlays, onlays, veneers, and bonding cover only the damaged portion of the tooth and leave the rest of the natural surface exposed.
Coverage decides everything else about a restoration. Full coverage redistributes chewing force across the whole tooth rather than concentrating it on weakened walls, which is why a crown is the standard choice for a tooth that has lost most of its structure. Partial coverage preserves more natural tooth, which is why a filling or an onlay is the better choice for a tooth that still has strong walls holding it together. Neither approach is universally better. The amount of healthy tooth structure remaining is what moves a tooth from one category to the other.
Tooth structure loss is common enough that most adults face this decision at some point. The CDC reports that 25.9% of adults aged 20 to 44 and 25.3% of adults aged 45 to 64 have untreated dental caries, and decay that goes untreated keeps expanding until the repair required moves up the coverage scale. Catching decay early is what keeps a small restoration in play, and it is the reason we place so much emphasis on cavity prevention at every visit.
Is a Dental Crown Considered a Restoration?
Yes, a dental crown is considered a restoration, and it belongs to the category of indirect restorations that are made outside the mouth and then bonded to the tooth. A crown restores the shape, size, strength, and function of a damaged tooth, which places it firmly in restorative dentistry rather than cosmetic dentistry.
Restorative dentistry divides into direct and indirect work. Direct restorations, meaning fillings and bonding, are shaped inside the mouth during a single appointment. Indirect restorations, meaning crowns, inlays, onlays, veneers, and bridges, are fabricated at a lab or milling unit and then fitted. Crowns improve appearance as a side effect of restoring form, which is where the confusion starts, but the reason we place dental crowns is structural. Long-term tooth protection is the goal, and the improved appearance comes along with it.
Are Dental Crowns Considered Major Restorative?
Yes, dental crowns are considered major restorative treatment, while fillings are classified as basic restorative treatment. The major classification reflects the laboratory work, the multiple appointments, and the degree of tooth preparation a crown requires, not the severity of the problem being treated.
Basic restorative work is completed chairside in one visit with materials shaped directly on the tooth. Major restorative work involves impressions, a laboratory or milling stage, and a second fitting appointment. Inlays, onlays, bridges, and dentures fall into the major category alongside crowns for the same reason. The classification is a description of the procedure type rather than a judgment about which restoration your tooth needs.
How Does a Dental Crown Compare to a Filling?
A dental crown covers the entire tooth and supports weakened walls, while a filling replaces only the decayed material inside a cavity and leaves the surrounding tooth structure to carry chewing force on its own. Crowns typically last 10 to 15 years or longer, while fillings generally serve 5 to 7 years in high-wear areas before needing repair or replacement.
Chewing force is the variable that separates them. A filling sits inside the tooth and depends on the walls around it staying intact. When those walls are thin, every bite flexes them slightly, and repeated flexing eventually cracks a cusp. A crown wraps the walls instead of relying on them, so the force presses the tooth together rather than pushing it apart. That single mechanical difference explains nearly every recommendation in restorative dentistry.
Why Do Dentists Recommend a Crown Instead of a Filling?
Dentists recommend a crown instead of a filling when too little healthy tooth structure remains to support a filling safely. The deciding factor is cuspal coverage, meaning whether the pointed chewing surfaces of the tooth still have enough thickness to survive years of biting force without fracturing.
Research backs the threshold rather than the instinct. A long-term study of extensive direct composite restorations found that premolars with two cusps replaced carried roughly three times the failure risk of premolars with only one cusp replaced. A meta-analysis covering 2,816 posterior composite restorations reached the same conclusion from a different angle, reporting significantly higher failure risk as the number of restored surfaces increased and in patients at high caries risk. More surfaces restored means less original tooth holding the restoration, and less original tooth means a shorter service life.
Service life is the practical question behind the recommendation. Replacing a filling removes a little more tooth structure each time, and a tooth can only absorb that cycle so many times before a crown becomes the only remaining option. Recommending full coverage earlier, at the point where the cusps are genuinely at risk, preserves more of the tooth over a lifetime than repeatedly enlarging a filling does.
How Long Does a Filling Last Compared to a Crown?
A filling lasts about 11 years on average for composite and more than 16 years for amalgam, while a crown lasts 10 to 15 years or longer with proper care. The averages sit closer together than most patients expect, but they describe different clinical situations, since fillings are placed in smaller cavities and crowns are placed in teeth that had already lost more structure.
Those figures come from a 2025 systematic review of eight studies published in Cureus, which found median survival beyond 16 years for amalgam restorations and about 11 years for composite. The same review identified different failure modes for each material: secondary caries drives composite failure, while fracture drives amalgam replacement. A separate systematic review and meta-analysis of posterior restorations found that well-placed composite fillings achieve annual failure rates of just 1% to 3%.
Failure mode matters more than the raw number. Crown research from Pjetursson and colleagues at the University of Bern calculated 95.6% survival at 5 years for metal-ceramic single crowns and 89.2% at 10 years for conventional tooth-supported restorations, with biological complications such as decay and loss of pulp vitality occurring more often than technical failures of the crown material. Both restoration types fail most often at the margin, where the restoration meets tooth, which is why daily cleaning influences the outcome more than the material choice does.
Can a Large Filling Be Replaced With a Crown?
Yes, a large filling can be replaced with a crown, and doing so is one of the most common reasons crowns are placed. A filling that occupies more than about half the width of the chewing surface leaves the remaining walls thin enough that a crown protects the tooth better than another filling would.
Replacement timing is a judgment made from the X-ray and the exam rather than from the age of the filling. An old restoration that is still sealed, with solid tooth structure around it, does not need to change. A filling with a gap at the margin, a crack line running from its edge, or a wall that flexes under pressure has already started the sequence that ends in fracture, and full coverage stops that sequence before the tooth splits.
How Does a Dental Crown Compare to an Inlay or Onlay?
A dental crown covers the entire tooth above the gumline, while an inlay fills the area between the cusps and an onlay covers one or more cusps without wrapping the whole tooth. Inlays and onlays sit in the middle of the coverage spectrum, preserving more natural tooth structure than a crown while providing more strength than a direct filling.
Both are indirect restorations, meaning they are fabricated outside the mouth from ceramic or composite and then bonded into a prepared space. That fabrication step is what gives them a tighter fit and better wear resistance than a large direct filling placed freehand. The distinction between the two is simple: an inlay stays within the cusps, and an onlay extends over at least one cusp tip.
Is an Onlay Better Than a Crown?
An onlay is better than a crown when the tooth still has strong, intact walls and only part of the chewing surface needs rebuilding. A crown is better when decay or fracture has compromised several walls, because partial coverage cannot reinforce a wall it does not cover.
Survival data shows both perform well inside their own indications. A systematic review and meta-analysis published in the Journal of Dental Research, covering 5,811 restorations, estimated survival for ceramic inlays, onlays, and overlays at 92% to 95% at 5 years and 91% at 10 years. Failure came most often from fracture or chipping at 4%, followed by endodontic complications at 3% and secondary caries at 1%. Those numbers sit alongside crown survival rather than below it, which is exactly the point: a well-chosen conservative restoration performs as well as a crown on a tooth that did not need full coverage.
Choosing correctly requires the remaining tooth structure to be evaluated in the mouth and on the X-ray, not estimated from symptoms. Inlays and onlays are not part of our treatment menu, and for patients whose teeth fall into that middle zone we discuss the full picture openly so the plan matches the tooth.
How Does a Dental Crown Compare to a Veneer?
A dental crown restores strength by covering the entire tooth, while a veneer improves appearance by covering only the front surface. The two answer different questions: a crown addresses structural damage, and a veneer addresses discoloration, small chips, gaps, or minor alignment on a tooth that is already healthy.
Preparation separates them as clearly as purpose does. A crown requires roughly 1 to 1.5 millimeters of reduction around the whole tooth. A veneer requires less than a millimeter, and only from the front surface. That difference means a veneer leaves the back and biting surfaces of the tooth untouched, which preserves structure but also means the veneer contributes almost nothing to the tooth’s ability to withstand chewing force.
Longevity is strong for both when they are correctly indicated. A 2025 meta-analysis published in the Journal of Esthetic and Restorative Dentistry, by Klein and colleagues, found pooled survival of 97.1% at 5 years and 96.1% at about 10 years for ceramic laminate veneers. Those results depend on bonding to healthy enamel, which is precisely why a veneer is not an option for a structurally compromised tooth. Patients exploring appearance-focused changes can review the full range of our cosmetic dentistry work and decide from there.
Can You Get a Veneer Instead of a Crown?
You can get a veneer instead of a crown when the tooth is healthy and the concern is appearance rather than strength. A veneer cannot substitute for a crown on a tooth that is cracked, heavily decayed, or treated with a root canal, because a thin shell bonded to the front surface does not hold the tooth together.
Back teeth follow a different rule than front teeth. Molars and premolars absorb the heaviest biting loads in the mouth, and veneers are rarely placed there for that reason. Front teeth carry lighter forces and are visible, which is why they are the usual location for veneers and why a front tooth with minimal damage is often better served by conservative treatment than by full coverage.
How Does a Dental Crown Compare to Dental Bonding?
A dental crown is a lab-fabricated cap bonded over the whole tooth, while dental bonding is tooth-colored composite resin applied and shaped directly on the tooth in a single visit. Bonding repairs small chips, closes minor gaps, and covers surface discoloration, while a crown rebuilds a tooth that has lost significant structure.
Bonding is the least invasive option on the entire spectrum. Most bonding work removes little or no healthy tooth structure, and the composite is cured with a light and polished in the same appointment. That speed and conservatism come with a trade-off in durability, since composite resin wears faster than ceramic and picks up stain over the years. For a small chip on a front tooth, dental bonding often delivers the result a patient wants without touching the rest of the tooth.
How Does a Dental Crown Compare to a Dental Bridge?
A dental crown restores one damaged tooth that is still in place, while a dental bridge replaces a tooth that is already missing by anchoring a replacement between two crowned teeth on either side of the gap. A crown treats a tooth you still have, and a bridge treats a space where a tooth used to be.
The two overlap because a bridge is built from crowns. The teeth flanking the gap are prepared and crowned, and those crowns carry the replacement tooth between them. Patients missing several teeth also consider removable options, and complete or partial dentures remain a practical choice for many of them. The right answer depends on how many teeth are missing, where they sat, and how the surrounding teeth are holding up.
What Can Be Done Instead of a Dental Crown?
Instead of a dental crown, a tooth can be treated with a filling, an inlay, an onlay, a veneer, or dental bonding, depending on how much healthy structure remains. Every one of those alternatives preserves more natural tooth than a crown, and every one of them requires the tooth to have enough intact wall structure to support a partial restoration.
The survival figures below come from the clinical research cited throughout this article, including the Cureus systematic review on filling longevity, the Journal of Dental Research meta-analysis on inlays and onlays, the Klein meta-analysis on ceramic veneers, and the Pjetursson reviews on crowns. Comparing them on one grid makes the pattern visible.
| Restoration | Coverage | Tooth removed | Main purpose | Typical survival | Usual failure mode |
|---|---|---|---|---|---|
| Dental crown | Entire tooth above the gumline | 1 to 1.5 mm all around | Structural strength | 10 to 15 years or longer; about 95% at 5 years | Decay at the margin |
| Filling | The cavity only | Decayed material only | Repair of small decay | About 11 years composite; over 16 years amalgam | Secondary caries in composite, fracture in amalgam |
| Inlay | Between the cusps | Damaged area plus a shaped seat | Moderate chewing-surface repair | 92% to 95% at 5 years; 91% at 10 years | Fracture or chipping |
| Onlay | One or more cusps | Less than a crown, more than an inlay | Partial cuspal protection | 92% to 95% at 5 years; 91% at 10 years | Fracture or chipping |
| Veneer | Front surface only | Under 1 mm from the front | Appearance | 97% at 5 years; 96% at about 10 years | Debonding or chipping |
| Bonding | The chip or gap only | Little to none | Small cosmetic repair | Shortest of the group | Wear, staining, chipping |
Reading down the coverage column explains the survival column. Restorations that cover more tooth carry more force, and restorations that carry more force protect the structure underneath them longer.
How Much Tooth Is Removed for a Dental Crown?
About 1 to 1.5 millimeters of tooth structure is removed around the entire tooth for a dental crown. That reduction creates the space the crown material occupies, and it is the single largest difference in preparation between a crown and every other restoration on the list.
Comparison puts the number in perspective. A veneer removes less than a millimeter and only from the front surface. An inlay or onlay removes the damaged area plus a shaped seat for the restoration to sit in. A filling removes the decayed material and nothing more. Preparation for a crown is greater because full coverage requires uniform thickness all the way around, and uneven thickness is where ceramic restorations crack.
Modern preparation is more conservative than it once was. Stronger materials like zirconia allow thinner walls than earlier ceramics did, which means less reduction for the same strength. The preparation still counts as a permanent change to the tooth, so we reserve it for teeth that genuinely benefit from full coverage rather than applying it as a default.
When Does a Tooth Need a Crown Instead of a Smaller Restoration?
A tooth needs a crown instead of a smaller restoration when the damage is too extensive for the remaining walls to support a partial repair. The clinical threshold is the amount of sound tooth structure left standing, particularly whether a continuous band of healthy tooth remains around the base of the preparation to grip the restoration.
That band of remaining tooth is called the ferrule, and its presence is the strongest predictor of whether a heavily restored tooth survives long term. A tooth with a complete ferrule and intact walls can often be restored conservatively. A tooth missing walls, or one where decay has run below the gumline, needs the wrap-around support only a crown provides. Recognizing which needs a crown is a call made from the exam and the X-ray together.
The situations that typically call for crown treatment are consistent from patient to patient:
- A large cavity that cannot be filled. Decay that has consumed most of the chewing surface leaves no solid wall to anchor a filling.
- A fractured or worn-down tooth. Cracks and heavy wear both reduce the tooth’s ability to absorb force on its own.
- A tooth treated with a root canal. Removing the nerve and the access opening leaves a back tooth measurably more brittle.
- A misshapen or severely discolored tooth. Full coverage restores contour and shade at the same time.
- A tooth anchoring a dental bridge. Supporting a replacement tooth requires the strength of full coverage.
Patients across Southwest Houston bring us teeth at every point on that list, and the conversation we have is always the same one: how much tooth is left, and what will protect the most of it for the longest time. When a tooth has deteriorated past the point where any restoration can save it, tooth extraction followed by a replacement option becomes the honest recommendation instead.
Can a Cracked Tooth Be Saved With a Crown?
Yes, a cracked tooth can usually be saved with a crown, as long as the crack has not extended below the gumline into the root. A crown holds the cracked segments together under biting pressure, which stops the crack from spreading and prevents the tooth from splitting.
Speed changes the outcome more than anything else with a cracked tooth. A crack confined to the crown portion of the tooth responds well to full coverage. The same crack left untreated for months migrates downward with every bite, and once it reaches the root the tooth is no longer restorable. Pain that appears on release of a bite, rather than on pressure, is the classic sign, and it is worth same-day care rather than a wait-and-see approach.
Is a Root Canal Always Needed With a Crown?
No, a root canal is not always needed with a crown. A crown is placed on a tooth with a healthy nerve whenever the damage is structural rather than infectious, and most crowns placed for fractures, wear, or large old fillings involve no root canal at all.
The relationship runs the other direction more reliably. A tooth that has already had root canal treatment usually does need a crown afterward, particularly a back tooth, because the access opening and the loss of internal moisture leave it more prone to fracture. A tooth needing a crown, by contrast, often has a perfectly healthy nerve that stays that way.
How Fragile Is a Tooth Without a Crown?
A tooth that has lost significant structure is far more fragile without a crown, and the difference is measurable. Research by Aquilino and Caplan at the University of Iowa College of Dentistry, published in the Journal of Prosthetic Dentistry, found that root-canal-treated teeth left without crowns were lost at 6.0 times the rate of teeth that received crowns.
A retrospective cohort study from the Faculty of Dentistry at Mahidol University traced the same pattern over time. Endodontically treated molars without crown coverage survived at 96% after one year, 88% after two years, and only 36% after five years. The first two years look reassuring, and then the curve collapses, because fracture is cumulative rather than immediate. The same study found that molars retaining the most tooth structure reached 78% survival at five years without a crown, which confirms the principle running through this entire comparison: remaining tooth structure, not the label on the treatment, determines how a tooth holds up.
What Are Dental Crowns Made Of?
Dental crowns are made of porcelain, porcelain fused to metal, zirconia, or gold and metal alloys. Each material trades appearance against strength differently, and the position of the tooth in the mouth usually decides which trade-off makes sense.
Porcelain delivers the most natural appearance and is the usual choice for teeth that show when you smile. Porcelain fused to metal pairs a metal substructure with a ceramic exterior, giving added strength for molars while keeping a tooth-colored surface. Zirconia is extremely durable and still highly aesthetic, which makes it a strong option for high-stress areas and back molars. Gold and metal alloys are used less often now, though they remain exceptionally long-lasting and are gentle on the opposing teeth they bite against.
Which Crown Material Is Strongest?
Zirconia and gold alloys are the strongest crown materials, with zirconia offering that strength in a tooth-colored form. Pure ceramic materials sit at the other end of the strength range, which is why they perform better on front teeth than on molars.
The clinical data shows that gap plainly. Pjetursson and colleagues reported 5-year survival of 96.4% for densely sintered alumina crowns and 87.5% for glass-ceramic crowns, and glass-ceramic crowns placed on posterior teeth dropped further to 84.4%. Back teeth generate the heaviest forces in the mouth, so material selection matters more there than anywhere else. We match the material to the tooth position, your bite, and whether you grind, rather than defaulting to one material for every case.
How Long Does It Take to Get a Dental Crown?
Getting a dental crown typically takes two visits spread across two to three weeks. The first visit prepares the tooth and places a temporary crown, and the second visit fits and bonds the permanent restoration.
Here is how the crown procedure runs at our office:
- Dr. Yu numbs the area and removes any decayed or damaged portions of the tooth.
- The tooth is shaped to the contour that will support the crown.
- Digital impressions capture the preparation, the neighboring teeth, and your bite.
- A temporary crown is placed to protect the prepared tooth while the lab fabricates the permanent one.
- At the second visit, the temporary comes off and the permanent crown is tried in for fit, contour, and shade.
- Once the bite checks out, the crown is bonded into place and polished.
The temporary phase asks for a few weeks of care, since temporary cement is intentionally weak so the crown lifts off easily at the second appointment. Chewing on the opposite side and avoiding sticky foods covers most of what that phase requires.
How Many Years Should a Dental Crown Last?
A dental crown should last 10 to 15 years or longer, and many patients keep the same crown for two decades or more. Daily cleaning at the crown margin, protection from grinding, and regular checkups decide where an individual crown falls inside that range.
Both the crown research and the filling research point at the same conclusion. The Pjetursson reviews found biological complications, meaning decay and loss of pulp vitality, occurring more often than material failures, and the Cureus review identified secondary caries as the leading cause of composite filling failure. Restorations rarely fail because the material gave out. They fail because bacteria reached the tooth structure at the edge. That makes home care the deciding variable regardless of which restoration you end up with, and it is the reason that CDC figure of 65.5% of adults attending a dental visit in the past year matters as much as any survival statistic on this page.
Consistent care changes the arithmetic. Reviewing crown longevity expectations with you before treatment means nothing about the result comes as a surprise years later, and a well-maintained custom crown keeps working as a tooth rather than as a repair on a countdown.
Frequently Asked Questions
Do Teeth Go Bad Under Crowns?
Teeth can go bad under crowns when plaque collects at the margin where the crown meets tooth structure. The crown material itself never decays, so any cavity on a crowned tooth starts at that edge and works inward. Daily brushing and flossing at the gumline, plus regular X-rays, catch the problem early enough to treat it before the crown needs replacing.
Does Getting a Dental Crown Hurt?
Getting a dental crown does not hurt, because local anesthesia numbs the tooth and surrounding tissue completely before any preparation begins. Most patients feel pressure and vibration rather than pain. Mild sensitivity for a few days afterward is normal and settles on its own, and Dr. Yu uses gentle techniques throughout to keep the appointment comfortable from start to finish.
Can a Dental Crown Be Placed on a Front Tooth?
Yes, a dental crown can be placed on a front tooth, and porcelain or zirconia is typically selected for those positions because of how naturally they reflect light. Front teeth carry lighter biting forces than molars, so material strength is less of a constraint and appearance takes priority. A front tooth with only minor damage is often better served by bonding or a veneer instead.
Will a Dental Crown Look Like a Natural Tooth?
A dental crown will look like a natural tooth when the shade is matched to your surrounding teeth and the material suits the position. Porcelain and zirconia reproduce the translucency and surface texture of enamel closely enough that most people never notice a well-made crown. We match crown shades to the teeth beside them so the restoration blends rather than announcing itself.
Can a Filling Be Used Instead of a Crown on a Back Tooth?
A filling can be used instead of a crown on a back tooth when the cavity is small and the surrounding walls are thick and intact. Once the restoration spans multiple surfaces or replaces a cusp, the failure risk climbs sharply. Research on posterior composites found premolars with two cusps replaced carried roughly three times the failure risk of those with one cusp replaced, which is where full coverage starts to make more sense.
Do Dental Crowns Need to Be Replaced Eventually?
Most dental crowns need to be replaced eventually, though the timeline stretches well past a decade with good care and some crowns serve for twenty years or more. Replacement is usually triggered by decay developing at the margin rather than by the crown material wearing out. Regular checkups catch margin problems while the underlying tooth is still healthy enough for a straightforward replacement.
The Bottom Line
Dental crowns and other restorations answer the same question at different scales. A filling repairs decay inside a cavity. An inlay or onlay rebuilds part of a chewing surface. A veneer or bonding improves how a healthy tooth looks. A crown covers the whole tooth and carries the force that the remaining walls no longer can. The right choice is the least invasive option that will still protect the tooth, which is why the amount of healthy structure left is the first thing we measure.
The research is consistent on one point across every restoration type: what fails is almost never the material, and almost always the seal at the edge. Whichever option fits your tooth, daily cleaning and regular checkups carry most of the weight in how long it lasts. If you have a tooth that is cracked, heavily filled, or sensitive under pressure, an exam and an X-ray will tell you exactly which end of the spectrum it sits on. Our Houston office is happy to walk you through the options without pressure. Reach Bright Value Dental at 713-668-1600 or check current appointment times when you are ready.